qCART™
Overcomes the Challenges of CAR T Cell Therapy
Chimeric antigen receptor T (CAR T) cell therapies have transformed the clinical treatment of certain hematological cancers. However, major obstacles have so far prevented the use of CAR T cell therapies to earlier lines and expanded indications. These include (1) adverse events such as on-target/off-tumor toxicity and cytokine release syndrome (CRS); (2) poor potency for solid tumors; (3) disease relapse due to antigen escape/heterogeneity in solid tumors or lack of CAR T cell persistence; and (4) high costs of CAR T cell manufacturing.
Clinical experience has revealed that CAR T cell attributes are crucial determinants of clinical activity. In particular, high levels of TSCM cells in the CAR T cell population are associated with the best clinical outcomes. This positive effect is probably in part because TSCM cells exhibit stem-like properties with high capacity for self-renewal and long lifespans, which may contribute to long-term persistence. In addition, the therapeutic efficacy of TSCM cells may be enhanced due to high metabolic fitness and a relative absence of senescence and exhaustion. Finally, TSCM cells encountering target antigens do not exhibit strong cytotoxicity but will expand and differentiate into highly cytotoxic TEM and TEFF cells. Thus, the kinetics of target cell cytotoxicity and release of cytokines may be slower and more sustained than cells at later differentiation stages. Together, these features of TSCM cells make them highly desirable in CAR T cell populations.
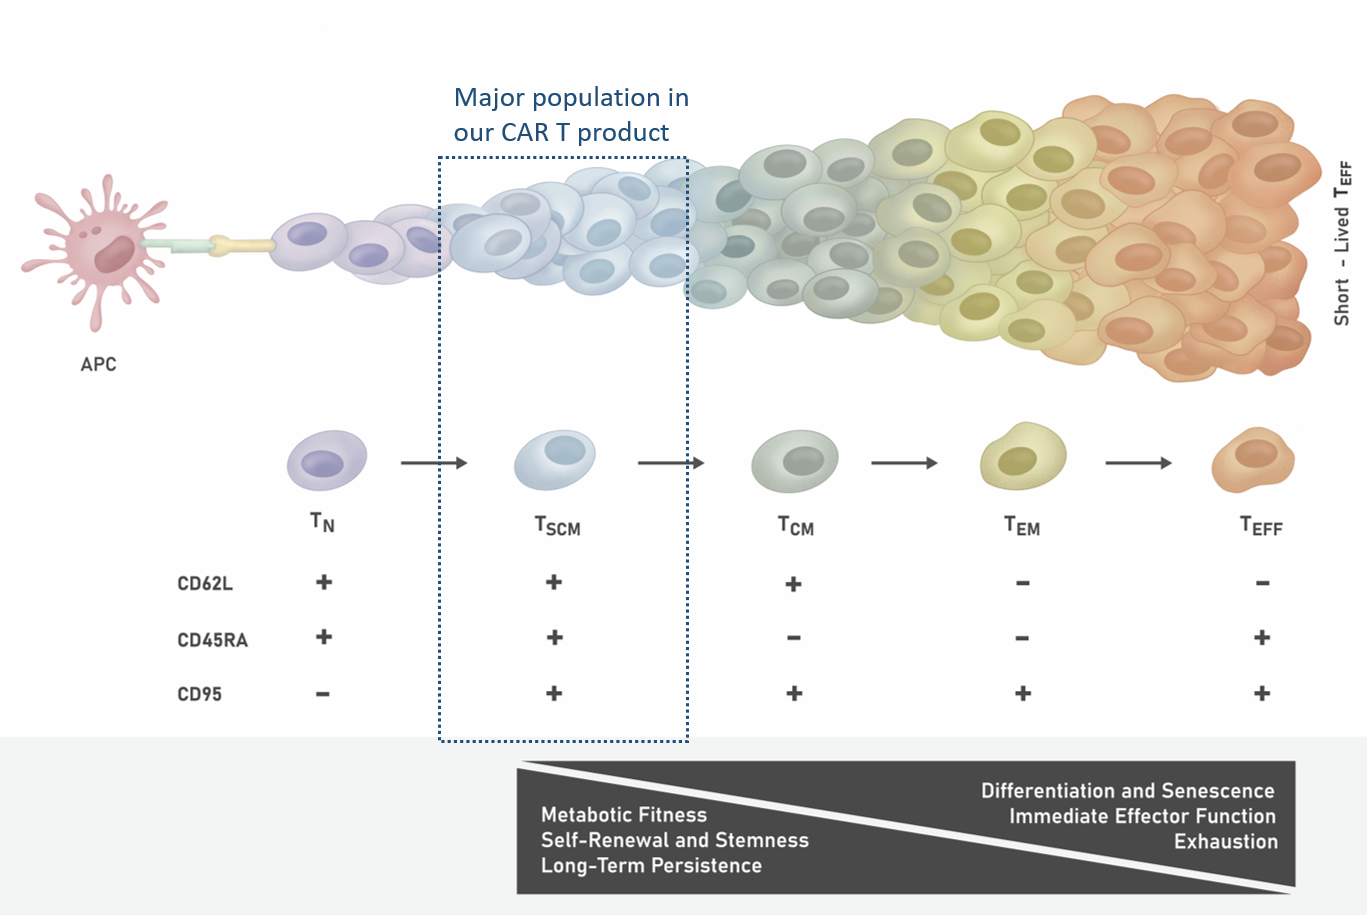
Figure 1. T cells differentiate upon antigen exposure. Following the activation of TN cells by antigens, long-lived TSCM and TCM cells are produced. These cells retain expression of CD62L and also begin to express CD95. Self-renewing TSCM and TCM cells in turn give rise to proliferating populations of shorter-lived TEM and TEFF cells. CAR TSCM cells are considered to be the most efficacious and safest CAR T cell population.
Several obstacles must be overcome to utilize CAR T cells for solid tumors, including (1) lack of CAR T cell trafficking to the tumor; (2) antigen heterogeneity of solid tumors; and (3) immunosuppressive tumor microenvironment (TME) which can adversely affect T cell fitness (e.g. differentiation, exhaustion, senescence, and survival). Technological breakthroughs are needed to overcome these hurdles.
Viral vectors have been widely used for production of CAR T cell therapies due to their highly efficient gene delivery and integration. However, CAR T cells generated with virus vectors have several limitations. These include (1) virus-associated safety concerns; (2) limited payload capacity; (3) low expansion capacity and low percentage of CAR⁺ T cells following transduction; (4) low CAR T cell persistence; and (5) high cost of manufacturing.
Virus-free systems can overcome most if not all of these hurdles. However, virus-free systems commonly require electroporation, which negatively affects viability and expansion capacity of the cells. Thus, electroporation presents a critical but addressable technical challenge for virus-free production of CAR T cells. Most importantly, an effective virus-free system must be able to integrate large multiplex transgenes into T cells, and expansion of the CAR T cells should be sufficient for clinical scale production of the drug product.
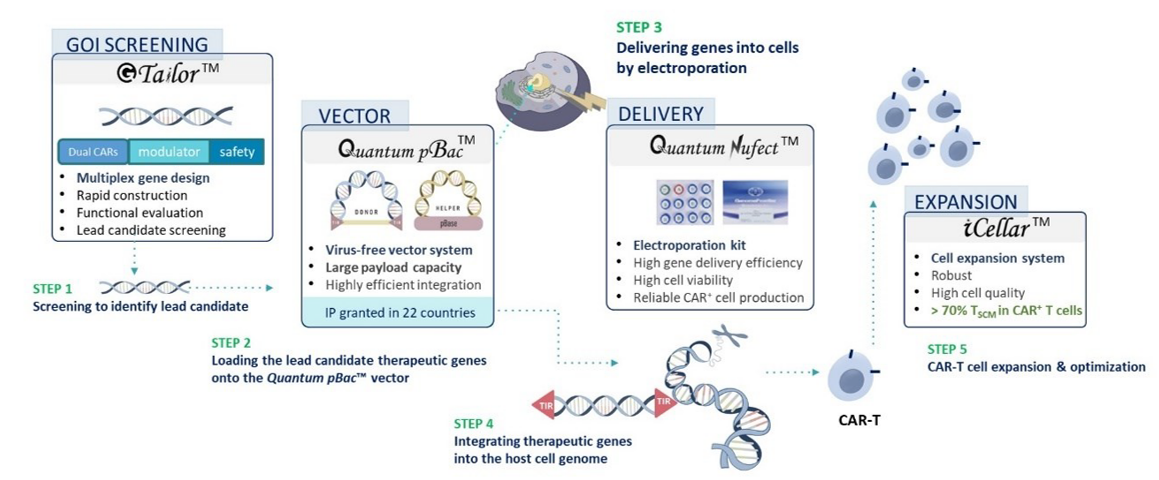
GenomeFrontier has developed Quantum CART (qCART™), a virus-free Quantum Engine™ for developing CAR T cell therapy that synergistically integrates four platforms:
(1) GTailor™: a rapid multiplex gene design, construction, and screening system for designing CAR T cells with (i) the ability to target to multiple tumor antigens; (ii) modulators for efficient CAR T cell trafficking and TME resistance; and (iii) a safety control to terminate treatment as needed.
(2) Quantum Nufect™: a robust gene delivery buffer system for introducing therapeutic genes into T cells, resulting in (i) reliable CAR T cell production while (ii) preserving high cell viability with preference in delivering into TSCM cell population.
(3) Quantum pBac™: a virus-free vector system with (i) a large payload gene integration capacity and (ii) high preference for TSCM genome integration.
(4) iCellar™: a robust cell expansion system for producing clinical-scaled CAR T cells with (i) high percentage of CAR⁺ TSCM cells and (ii) enhanced fitness.
Collectively, qCART™ enables timely (~10 days) and cost-effective manufacturing of CAR T cells at clinical scale (1 - 3.5x10⁹ cells/L). Crucially, qCART™ yields highly desirable CAR T cells with high proportions of CAR⁺ TSCM cells. Data from qCART™ production of GF-CART01 demonstrate the advantages of the system.
Table 1. Comparison of CAR T cell production using perfusion or fed batch culture vessels. CAR T cells were cultured in either the conventional plates (perfusion) or G-Rex vessels (fed batch). The percentages of CAR⁺ T cells, expansion fold changes, and distributions of CD4⁺ and CD8⁺ CAR⁺ T cell subsets are shown. N = 6 healthy donors.
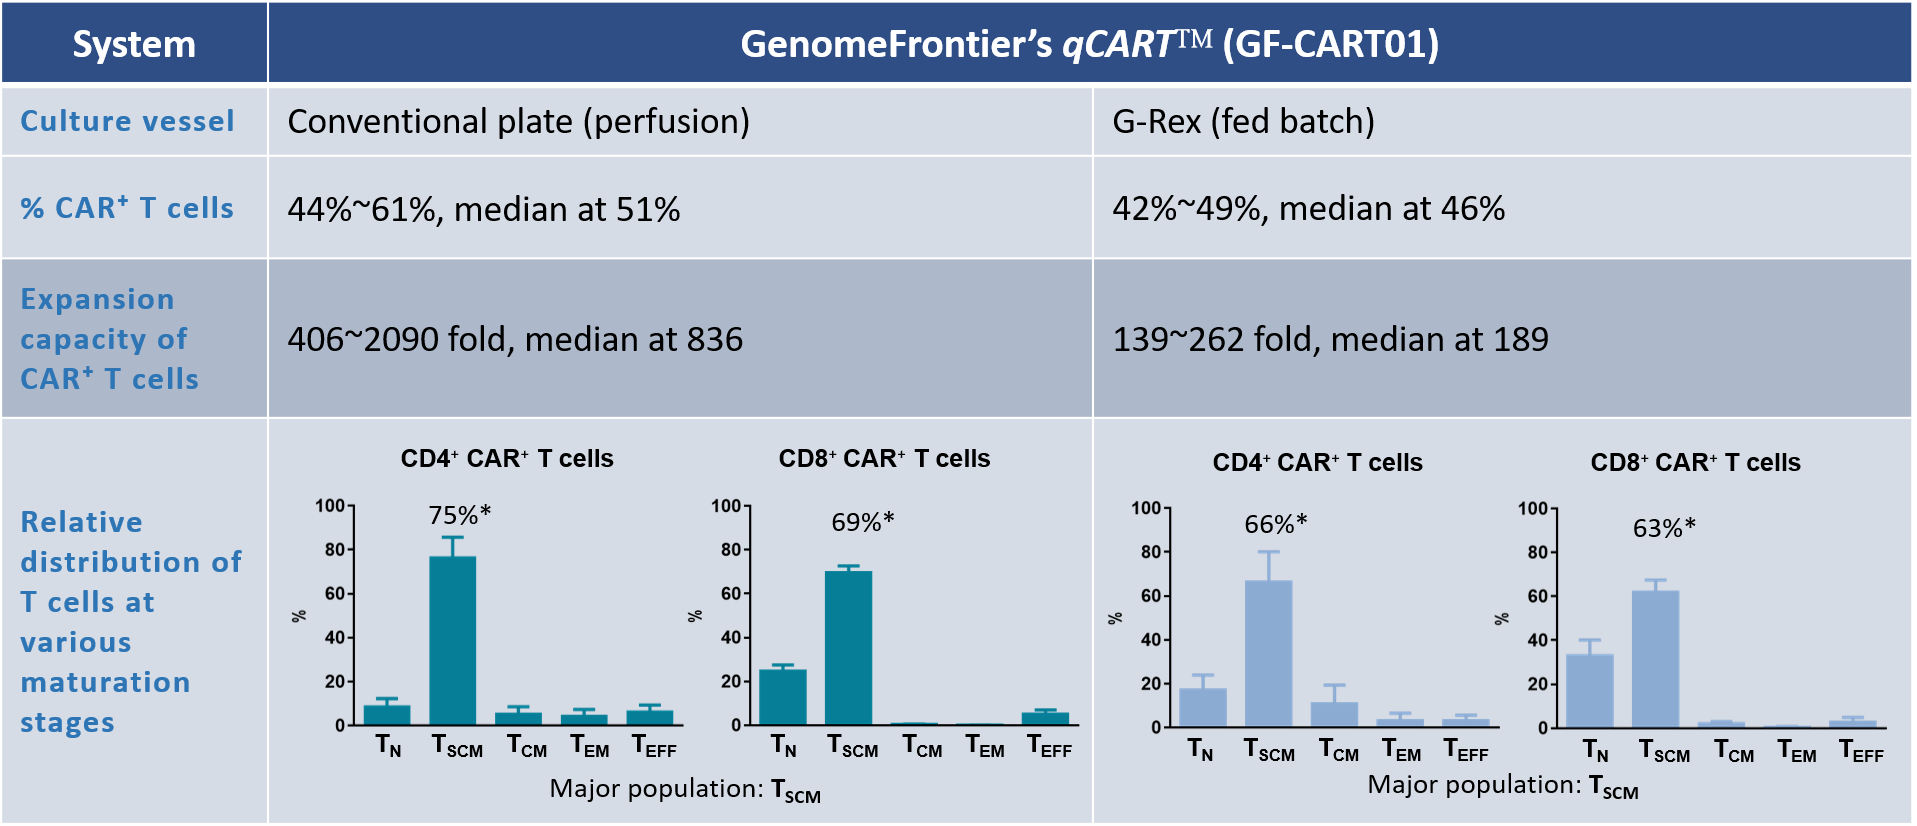
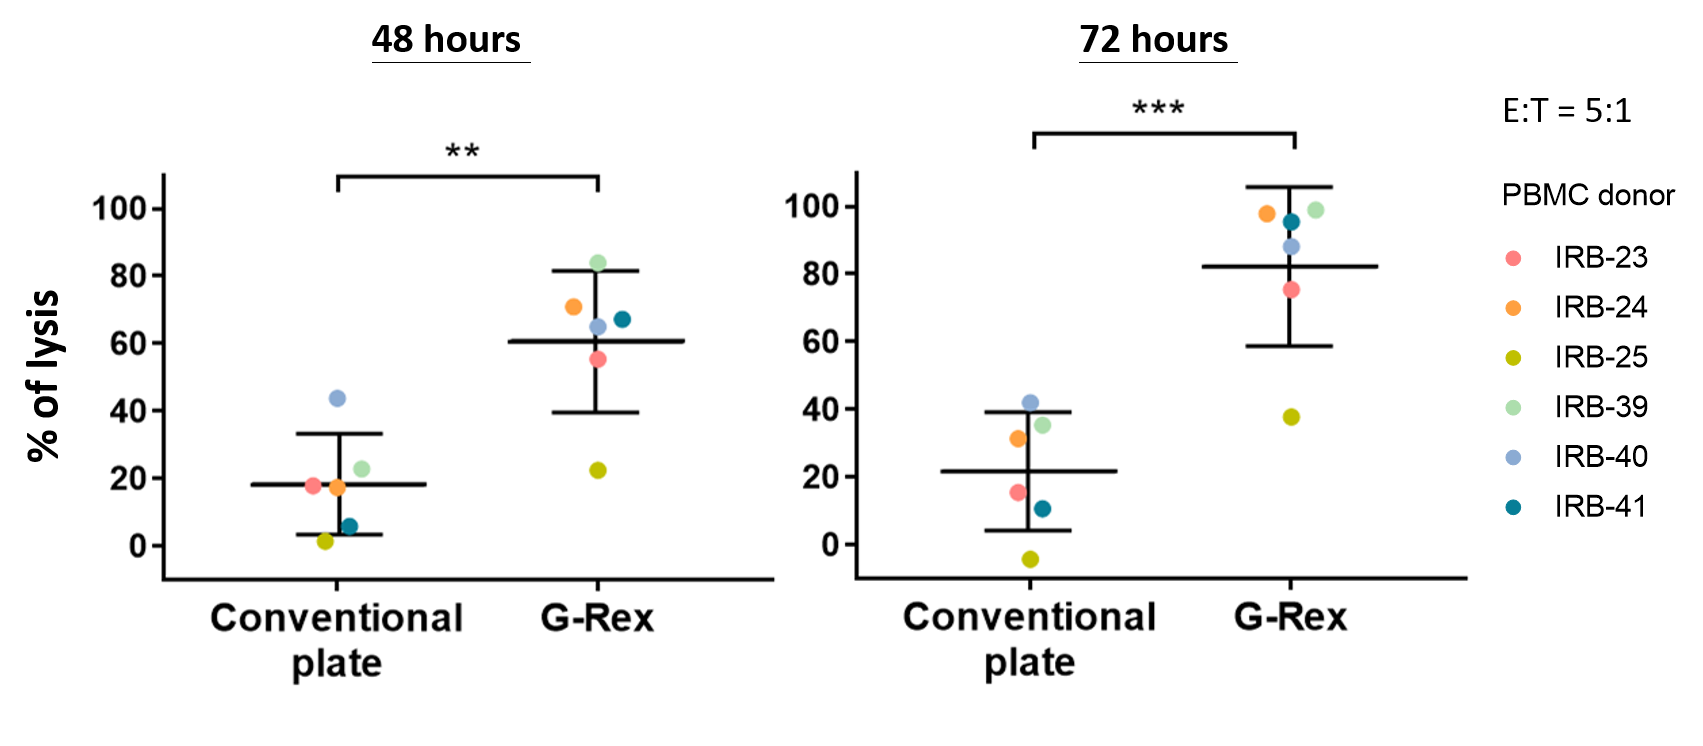
Figure 2. CAR T cells expanded in G-Rex vessels exhibit high cytotoxicity. An in vitro functional analysis was performed on CAR T cells cultured in either conventional plates (perfusion) or G-Rex vessels (fed batch). Thawed CAR T cells were assessed for cytolytic activity using Celigo image cytometry. Cytotoxicity of CAR T cells after 48 or 72 hours of co-culture with Raji-GFP/Luc target cells (E:T ratio 5:1). Data are from 6 healthy donors. Horizontal lines represent the mean % lysis of target cells by CAR T cells. **p < 0.01; ***p < 0.001.
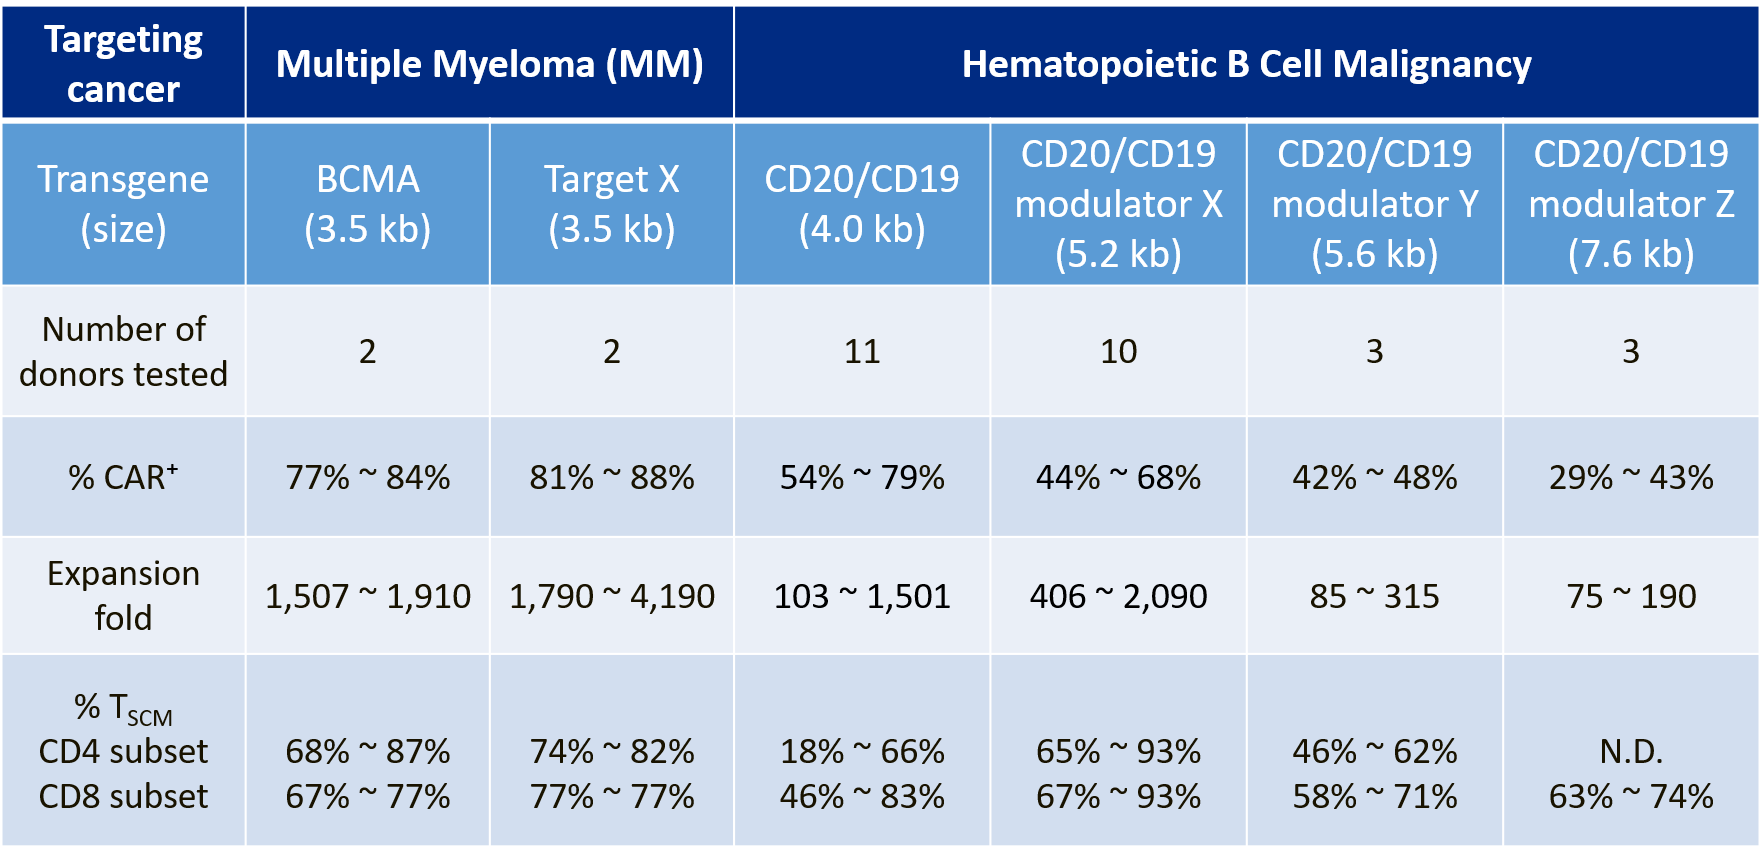
Table 2. CAR T cells can be produced against different targets and with various transgene sizes. CAR T cells can be produced using transgenes of different sizes. Donor T cells were nucleofected with Quantum Quantum pBac™ carrying transgenes with sizes ranging from 3.5 kb to 7.6 kb. The percentages of CAR⁺ T cells, expansion fold changes, and distributions of CD4⁺ and CD8⁺ CAR⁺ T cell subsets are shown.